Treatment Comparison
EBOO vs DFPP: Understanding the Difference
EBOO and DFPP are sometimes mentioned in the same conversation because both circulate blood through an external circuit. Beyond that similarity they are separate procedures with different mechanisms, different equipment and different planning requirements. Neither is a substitute for the other, and neither is universally preferable.
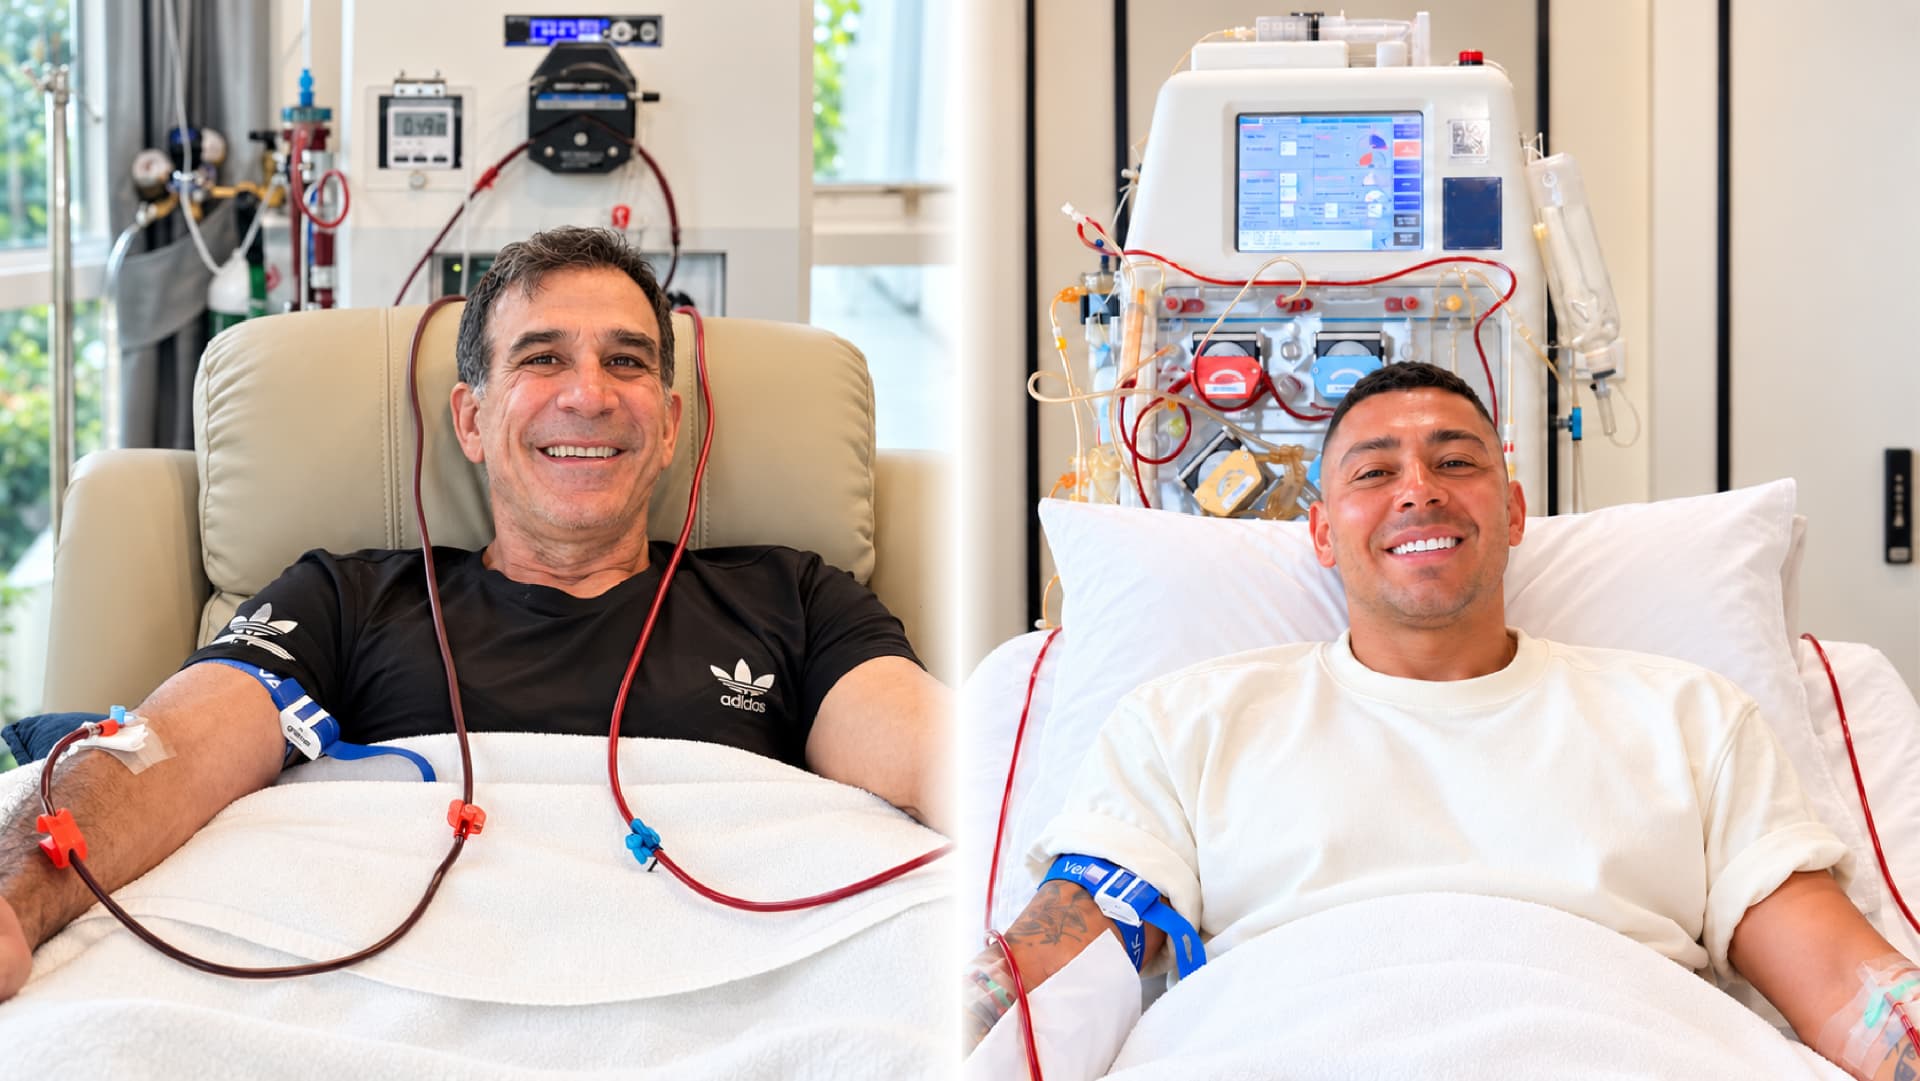
Two distinct procedures
EBOO passes blood through a filter unit where oxygen and ozone are introduced at controlled settings before the blood is returned. Nothing is separated out of the blood for disposal.
DFPP first separates plasma from the cellular components, then passes that plasma through a second filter chosen for its pore characteristics, before the plasma and cells are recombined and returned. The purpose, consumables and monitoring requirements are therefore different from EBOO.
Side-by-side comparison
The table below summarises where the two procedures diverge. It is written to support a conversation with a physician, not to help you self-select a treatment.
| EBOO | DFPP | |
|---|---|---|
| Core process | Blood circulates through a closed circuit and returns without component separation | Plasma is separated from cells, filtered a second time, then recombined and returned |
| Main treatment mechanism | Controlled oxygenation and ozonation of circulating blood | Selective filtration of plasma according to the filter characteristics chosen |
| Typical session approach | Single supervised session, repeated only if the physician advises it | Session planned around laboratory findings, with volumes defined in advance |
| Medical assessment | History, medicines, vascular access and relevant blood tests reviewed | Usually more detailed laboratory assessment, including clotting and protein-related markers |
| Treatment planning | Reviewed after each session rather than fixed as a set course | Planned individually and often reviewed against repeat testing |
| Approximate duration | Around one hour for the procedure, plus preparation and observation | Commonly longer, as separation and filtration proceed at a controlled rate |
| Suitability | Determined case by case after physician assessment | Determined case by case, with a lower threshold for declining or deferring |
Why neither is presented as better
The two procedures address different things, so ranking them has no clinical meaning. A description that suits one patient's circumstances may be irrelevant or inappropriate for another, and comparative marketing claims are not a reliable basis for a medical decision.
The evidence base also differs between them, and differs again depending on the setting in which each is used. Ask specifically which evidence applies to your situation.
How the doctor decides which option to discuss
During consultation the physician weighs your goals against your diagnoses, medicines, laboratory findings, vascular access, bleeding or clotting risk and any recent procedures. The outcome may be a recommendation for one option, a suggestion to investigate further, referral for standard medical care, or advice that no procedure is appropriate at this time.
- Choosing between them from a website description is not appropriate.
- A second opinion from your treating physician is welcome, particularly with ongoing conditions.
- Individual responses vary and no outcome is guaranteed for either procedure.
Practical differences for international visitors
Because DFPP planning may involve laboratory work and a longer appointment, it usually needs more lead time than an EBOO session. If you are travelling to Bangkok, sharing your records with the Care Team before arrival allows the physician to review them and helps the clinic tell you realistically how many days to allow.
Related program
EBOO Therapy & DFPP Plasmapheresis
Explore the program overview, then book a physician consultation to discuss individual suitability.
Medical Disclaimer
This article is for educational purposes and does not replace medical consultation, diagnosis or care. Individual suitability must be assessed by a physician. Treatment plans are personalised, individual responses vary and no outcome is guaranteed.

