DFPP
What Is Double Filtration Plasmapheresis (DFPP)?
Double filtration plasmapheresis is often abbreviated to DFPP. The name describes the process precisely: blood is separated into plasma and cells, the plasma then passes through a second filter, and the components are returned together. This article explains each stage in plain language.
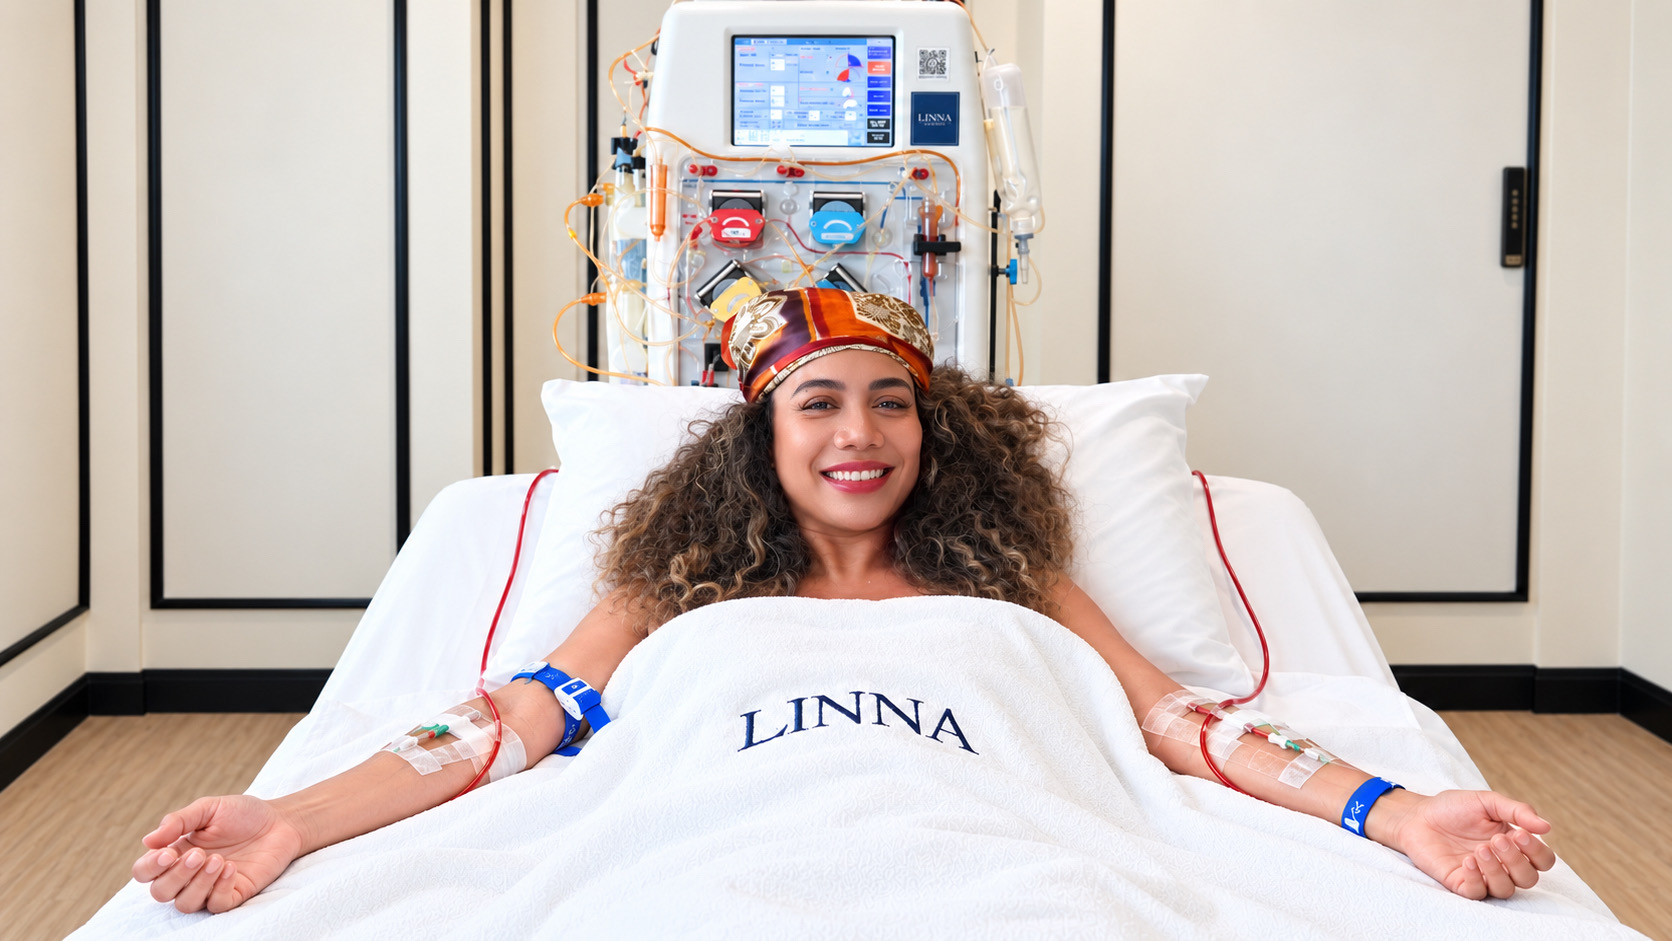
What DFPP means
DFPP is an extracorporeal procedure, meaning part of the circulation is handled temporarily outside the body through sterile tubing and filters. The word double refers to the two filtration stages rather than to two separate appointments.
It is performed under medical supervision with dedicated apparatus and single-use consumables. It does not remove all toxins from the body, and it is not a treatment for disease in general terms.
How plasma separation works
In the first stage, blood entering the circuit reaches a plasma separator. Red cells, white cells and platelets are too large to pass through its membrane and continue along their own path, while the liquid plasma passes through and is directed to the second stage.
Flow rate and the volume processed are set by the clinician, and anticoagulation within the circuit is managed carefully so blood moves smoothly without clotting in the lines.
What the second filtration stage does
The separated plasma meets a second filter with a smaller pore size. Larger plasma molecules are retained by this filter while smaller molecules, including a substantial proportion of albumin, continue through with the fluid that will be returned.
Filter selection is a clinical decision based on what the physician intends to address and on your laboratory findings. This selectivity is the defining feature of DFPP and the reason it requires individual planning.
How filtered plasma is returned
The filtered plasma is recombined with the cellular components and returned through the second access point. Because much of the plasma volume is preserved, replacement fluid requirements are generally lower than with procedures that discard the full plasma volume.
Fluid balance, blood pressure and how you are feeling are monitored throughout, and the team can pause or adjust the process at any point.
Why laboratory assessment may be required
Testing is not a formality. It informs whether the procedure is appropriate at all, how it should be configured, and what should be rechecked afterwards.
- Blood count and clotting markers relate to bleeding and clotting risk within the circuit.
- Protein and albumin levels help the physician plan volumes and replacement fluid.
- Kidney and liver markers give context for fluid handling and overall fitness for the procedure.
- Additional tests may be added or omitted according to your history; the panel is selected individually.
What to expect before, during and after treatment
Before: a consultation, record review and any testing the physician requests. You will be told what to eat and drink, which medicines to continue, and how long to allow for the appointment.
During: you remain seated or reclined with staff present. The procedure commonly takes longer than a simple infusion because separation and filtration run at a controlled rate.
After: a period of observation, individual aftercare instructions and advice on which symptoms to report. Rest on the day of treatment and avoid strenuous activity.
Who may require additional medical screening
Some circumstances call for more detailed screening, specialist input or a decision to defer. These include bleeding or clotting disorders, significant cardiac or kidney disease, active infection, difficult vascular access, low body weight, anaemia, pregnancy or breastfeeding, and use of anticoagulant medication.
Being asked for further assessment is a sign that the process is working as intended, and a recommendation against treatment is a legitimate outcome of consultation.
How DFPP differs from traditional plasma exchange
In conventional therapeutic plasma exchange, the separated plasma is discarded and replaced with donor plasma or albumin solution. DFPP instead filters the separated plasma and returns most of it, which usually reduces the volume of replacement fluid needed.
Each approach has its own clinical uses, advantages and limitations, and neither is universally superior. Which is appropriate, if either, is a decision for the supervising physician based on your individual assessment.
Related program
DFPP Plasmapheresis
Explore the program overview, then book a physician consultation to discuss individual suitability.
Medical Disclaimer
This article is for educational purposes and does not replace medical consultation, diagnosis or care. Individual suitability must be assessed by a physician. Treatment plans are personalised, individual responses vary and no outcome is guaranteed.

